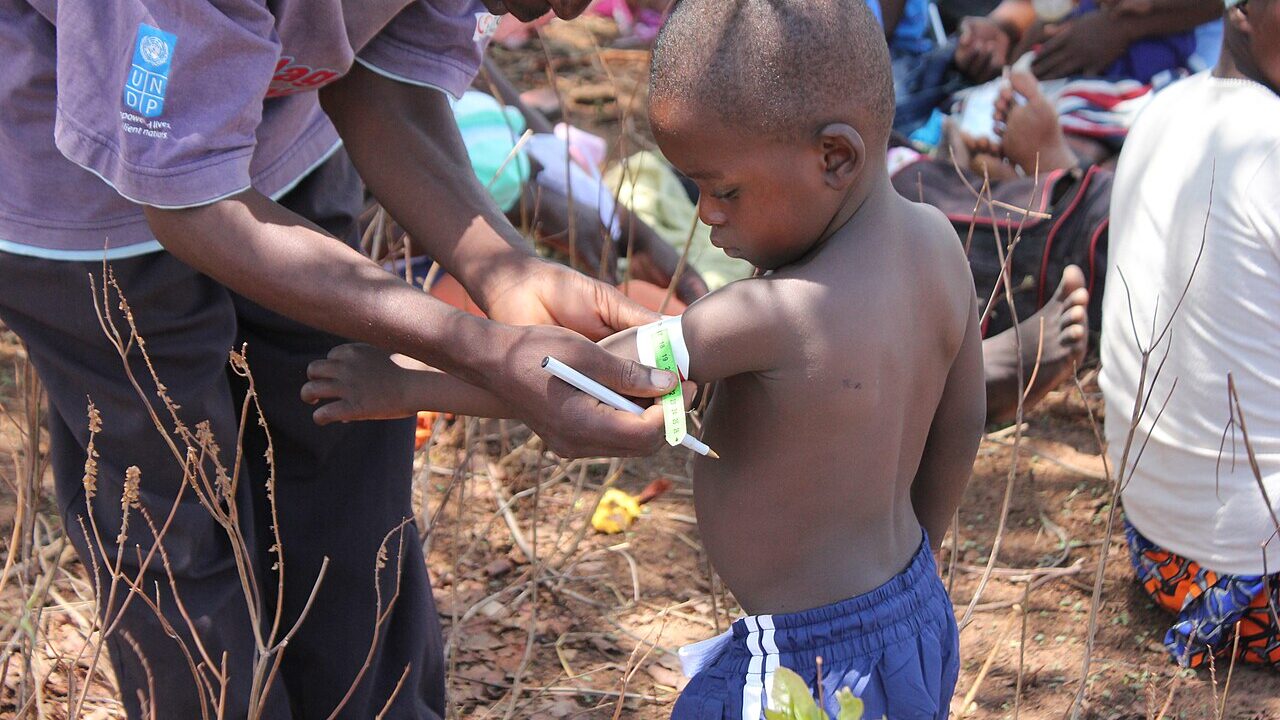
On October 9, 2026, the World Health Organization launched its 2026 global appeal, saying it needs approximately $1 billion to sustain life-saving health services for the millions of people living through humanitarian crises and conflicts.
The appeal’s arithmetic, as WHO presents it, covers 36 health emergencies — including 14 at Grade 3, the agency’s highest level of activation — against an estimated 239 million people facing humanitarian need. A billion dollars is simultaneously an enormous sum and a visibly inadequate one, divided as it must be across cholera responses, conflict-zone hospitals, vaccination campaigns in displacement camps and the surveillance systems meant to catch the next outbreak in its first district. WHO’s case to donors rests on the asymmetry its officials repeat in every cycle: health response is most needed exactly where security and logistics make it most expensive, and cheapest — always — before the emergency peaks.
The funding model is the appeal’s chronic condition. Assessed contributions from member states cover a minority of WHO’s emergency work; the rest is voluntary, earmarked and late, arriving after the cameras that loosened it have moved on. Agencies have adapted by pricing prevention in the treasury’s language — the contained outbreak against the globalised one — but the structural gap between the appeal’s figures and the pledges they draw has become a fixture of the system rather than an embarrassment within it.
The pledge season
Donor conferences in the coming weeks will reveal which of the 36 emergencies are funded at plan and which are triaged silently. NewsWibe’s Health & Science Desk will follow the pledges, the funding percentages and the first allocations as WHO reports them.
The appeal is also a map of the world’s failures ranked by a single criterion: where being sick has become, additionally, a logistical problem. Thirty-six emergencies is not a workload; it is a verdict on every system upstream of the clinic door.